Inclusions, sickling screens, erythrocytosis and the ESR
15 min
Skills you'll build4 skills
- Choose an iron stain to confirm suspected Pappenheimer bodies
- Report a positive Hb S solubility screen without calling trait or disease
- Choose between a repeat count, EPO, and JAK2 V617F for a raised hemoglobin
- Recognize how citrate ratio, anemia, tube tilt, and temperature change a Westergren ESR
At the bench: Relate red cell indices and morphology to the anemia workup
Try first
Get the idea
Use the explanation to check your first decision.
Confirm iron before you report it
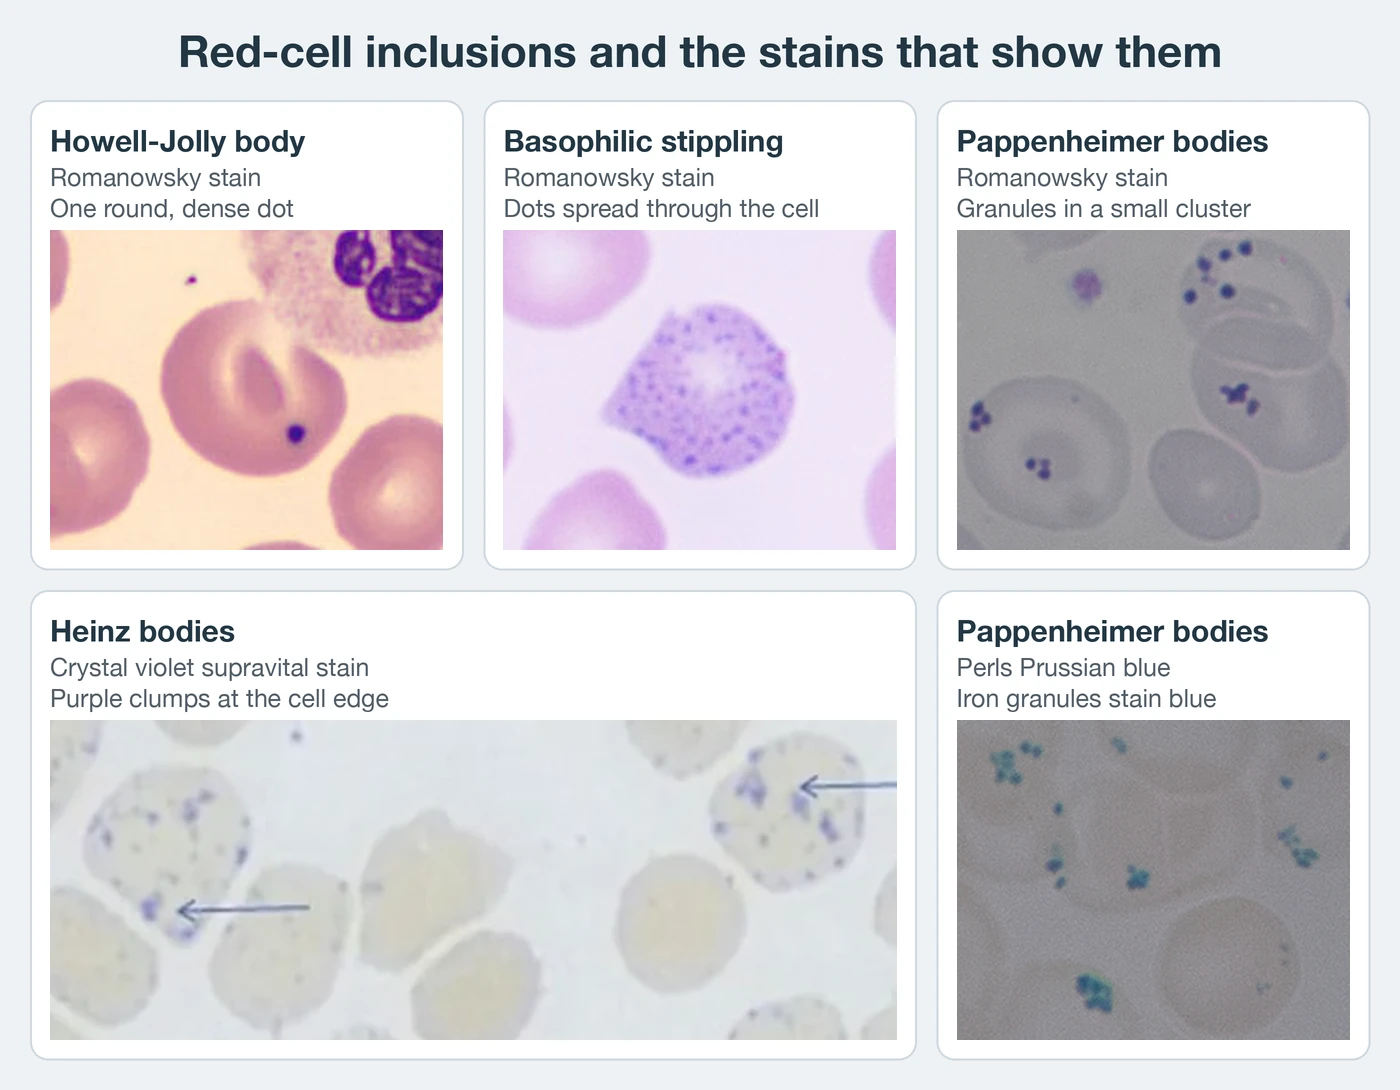
Pappenheimer bodies, Howell-Jolly bodies, and basophilic stippling can all look dark on a Wright-stained film. Only Pappenheimer bodies contain iron, and a Prussian blue stain confirms the iron.1 Reporting iron granules without that stain can mistake another inclusion for the iron-loaded cells of sideroblastic anemia, so clustered granules are stained before they are reported.
Hemoglobin variant screening
A positive Hb S solubility screen shows that a sickling hemoglobin is present in some amount. Trait and sickle cell disease both give a positive result, so the screen cannot distinguish them, and every positive result goes on to electrophoresis or high-performance liquid chromatography (HPLC).2,3 A negative screen also does not exclude a sickling hemoglobin in severe anemia, in a young infant with a large Hb F fraction, or after recent transfusion.2
Erythrocytosis workup
A raised hemoglobin is confirmed against prior results before anything else is ordered, because plasma-volume loss, hypoxia, and other causes can raise it without a true increase in red-cell mass.4 Serum erythropoietin (EPO) is the next test. A subnormal result supports a primary process, and a normal or increased result supports a secondary cause. JAK2 V617F is tested when polycythemia vera is plausible. Skipping the EPO step sends a patient with a plausible secondary cause to molecular testing that may not be needed.4
ESR specimen and technique
The Westergren reference method requires blood diluted 4:1 with citrate or saline. A coagulation tube has a 9:1 ratio, which is wrong for this method.5 Anemia raises the result without any change in inflammation. A tilted tube, vibration, or high temperature also raises it.5,6 Interpret every ESR with the hematocrit.
Follow the bench demonstration
Sources for this step
References
- Keohane EM, Preston MM, Mirza KM, Walenga JM, eds. Rodak's Hematology: Clinical Principles and Applications. 7th ed. Elsevier; 2025. Accessed September 26, 2026. https://www.us.elsevierhealth.com/rodaks-hematology-9780323936507.html
- Mayo Clinic Laboratories. Sickle solubility, blood (SDEX). Clinical Information, Cautions, and Method Description. Accessed September 26, 2026. https://www.mayocliniclabs.com/test-catalog/Overview/9180
- Bender MA, Carlberg K. Sickle cell disease. In: Adam MP, Bick S, Mirzaa GM, et al, eds. GeneReviews. University of Washington, Seattle; 2003. Revised February 13, 2025. Accessed September 26, 2026. https://www.ncbi.nlm.nih.gov/books/NBK1377/
- Noumani I, Harrison CN, McMullin MF. Erythrocytosis: diagnosis and investigation. Int J Lab Hematol. 2024;46(suppl 1):55-62. doi:10.1111/ijlh.14298
- Jou JM, Lewis SM, Briggs C, Lee S-H, De La Salle B, McFadden S. ICSH review of the measurement of the erythrocyte sedimentation rate. Int J Lab Hematol. 2011;33(2):125-132. doi:10.1111/j.1751-553X.2011.01302.x
- Kratz A, Plebani M, Peng M, Lee YK, McCafferty R, Machin SJ. ICSH recommendations for modified and alternate methods measuring the erythrocyte sedimentation rate. Int J Lab Hematol. 2017;39(5):448-457. doi:10.1111/ijlh.12693
- Palmer L, Briggs C, McFadden S, et al. ICSH recommendations for the standardization of nomenclature and grading of peripheral blood cell morphological features. Int J Lab Hematol. 2015;37(3):287-303. doi:10.1111/ijlh.12327
Watch one
Read each decision and its explanation.
A repeat CBC confirms a hemoglobin of 18.6 g/dL, unchanged from a result 3 months ago. The patient has no history of dehydration, smoking, high altitude, or lung or heart disease. What is the next test?
- Confirm persistence. The repeat CBC matches the result from 3 months ago.
A persistent increase is confirmed against prior results before further testing is ordered.
- Review the history. There is no dehydration, smoking, altitude, or cardiopulmonary disease to explain a secondary cause.
Ruling out plasma-volume loss and hypoxia narrows the differential before a specific test is chosen.
- Order serum erythropoietin (EPO) as the next test.
Serum EPO distinguishes a primary from a secondary process before molecular testing is ordered.
- A subnormal EPO result would support a primary process and would make JAK2 V617F testing the next step.
A subnormal EPO makes polycythemia vera likely enough to test for.
Your turn
Use it
Read the case evidence, then make each decision. The step is complete without it.
- A man, MRN 0392718, splenectomized 5 years ago after trauma, reports fatigue and joint pain.
- The emergency department orders a CBC with film, an ESR, and a sickle solubility screen.
- The film shows several red cells with small, clustered, dark granules.
- The ESR specimen arrives in a 9:1 sodium citrate coagulation tube.
- The sickle solubility screen returns positive.
None of the three findings can be reported as it stands. The clustered granules need a Prussian blue stain before they are reported as iron. The ESR specimen has a 9:1 ratio, so it is rejected. The positive sickle screen needs fractionation before trait or disease is reported.
Review missed questions
For reference
Sources checked